When Everyone Else's Schedule Restarts and Yours Has to Absorb It
Quick Answer: When the calendar refills in September, caregiving time doesn’t shrink - everything else expands around it, and the thing that gets cut is invariably your own maintenance. The most effective protection is making your recovery time a scheduled, named commitment rather than the gap between other people’s needs, and choosing a version short enough to survive a bad week. Ten protected minutes daily beats an hour you’ll never get.
The caregiving didn’t get lighter. Everything around it got heavier, all in the same fortnight.
This is one of the two or three hardest points in a caregiver’s year, and it’s worth planning for rather than absorbing.
This is general information, not medical advice. Persistent exhaustion, low mood, or physical symptoms deserve a conversation with a doctor - caregivers routinely delay this and shouldn’t.


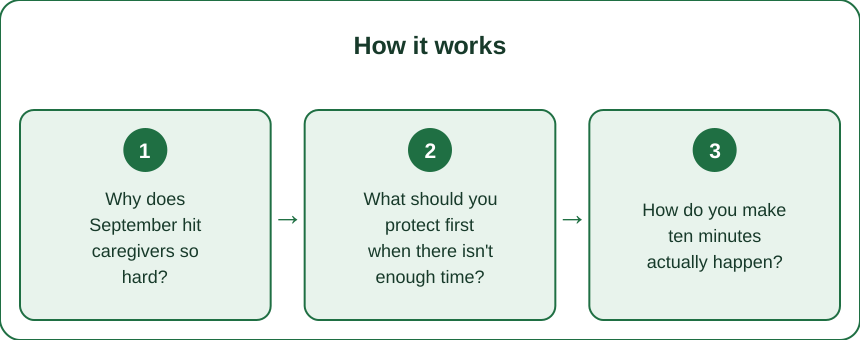
Why does September hit caregivers so hard?
Several loads arrive together and none of them replaces an existing one.
Caregiving is a fixed baseline. It doesn’t scale down when the rest of life scales up. Everything September adds - school schedules, restarted appointments, work intensity, other people’s routines - stacks on top of an already full load.
Medical calendars restart too. Practices and specialists that ran reduced summer schedules resume, which produces a cluster of appointments in a short window. The person you care for often has more appointments in September than in July and August combined.
Your buffers disappear. Summer’s flexibility - the neighbour who was around, the relative visiting, the general looseness of August - all ends at once. The informal support network that quietly absorbed overflow goes back to its own life.
And the cognitive load is the invisible part. Coordinating multiple schedules that all changed simultaneously is genuinely demanding work. It doesn’t look like anything from outside, and it consumes real capacity.
Why naming this matters: caregivers commonly interpret September exhaustion as personal failing - not managing well, not coping. It’s a genuine spike in demand at a moment when informal support is at its lowest. The response is structural, not attitudinal.
What should you protect first when there isn’t enough time?
In order, when you can only defend a few things.
1. Sleep timing, above everything. Not duration, which you may not control - timing. A consistent sleep and wake window stabilises energy and mood more than any other single factor. Going to bed at wildly different times is more damaging than going to bed slightly late consistently.
2. One protected block, daily, however short. Ten minutes is a legitimate answer. The point is that it exists reliably, not that it’s long enough to accomplish anything.
3. Movement that requires no logistics. Anything needing travel, changing, or booking will be the first casualty. Five minutes of strength work at home survives a bad week; a gym class doesn’t.
4. One meal you don’t have to think about. Decision fatigue is heaviest around food. Fixing breakfast as an identical, no-decision meal removes one recurring drain at the time of day when you’re least resourced.
5. One connection point a week. A phone call, a message thread, anything. Isolation is one of the strongest predictors of caregiver burnout, and it creeps in without any decision being made.
What to consciously let go: the standard of everything that isn’t load-bearing. A less tidy house, simpler meals, unanswered non-urgent messages. Deliberately lowering a standard is a decision; letting everything slide while feeling bad about it is not.

How do you make ten minutes actually happen?
By treating it structurally rather than as something you’ll fit in.
Attach it to an existing fixed point. Same principle as any habit - after the morning medication round, after drop-off, after they’ve settled for the evening. Attached time survives; floating time doesn’t.
Name it in the calendar. Not “free time” - a specific named block. Unnamed time gets reallocated, by you as much as by anyone else, because it doesn’t look like a commitment.
Have a defined default so it doesn’t require a decision. When the ten minutes arrives and you have to choose what to do with it, it frequently gets spent on a chore instead. Decide in advance: the walk, the stretch sequence, sitting with tea and no phone.
Three ten-minute options worth having ready:
- Physical reset - 10 slow squats, 10 wall push-ups, 30 seconds of a doorway chest stretch, 5 shoulder rolls. Counters the specific pattern of caregiving strain - forward-rounded, one-sided lifting
- Nervous system reset - extended-exhale breathing, in for 4 out for 6, for three minutes, then sit quietly
- Outdoors - ten minutes outside, ideally in morning light. Helps sleep timing and mood, and it’s the highest-value version if you can only pick one
Say it out loud to the household. “I’m taking ten minutes at seven” is far more robust than hoping for a gap. Most caregivers under-ask, and most households respond fine to a specific, small, stated request.
What Nobody Tells You About Caregiver Time
Five things that change how you approach it.
The time doesn’t exist to be found - it has to be taken. Waiting for a gap means waiting indefinitely, because caregiving expands to fill whatever’s available. The ten minutes has to be removed from something else deliberately, and accepting that is the step most people skip.
Guilt peaks precisely when you most need the break. The moment you sit down is when the mental list arrives. Recognising it as a predictable reflex rather than accurate information about your obligations makes it much easier to sit through - it typically fades within a few minutes.
Small consistent beats large occasional, by a wide margin. A weekend away every few months doesn’t offset daily depletion. Daily micro-recovery does more for sustained capacity than periodic large breaks, though both help.
Asking for specific help works far better than asking for help. “Can you take Thursday afternoons?” gets a yes or a no. “Let me know if you can help” reliably produces nothing - not because people don’t care, but because it hands them a planning problem.
Your own health appointments are the first thing cancelled and the most costly to lose. Caregivers routinely defer their own screening and check-ups. Booking your own appointments at the same time as theirs - same day, same trip where possible - is the single most practical workaround.
FAQ: Caregiver Schedule Questions, Answered
How do I ask for help without feeling like a burden?
Ask for something specific, small and time-bound - a named task on a named day. People are far more likely to say yes to “can you sit with her Tuesday 2-4” than to an open-ended request, and a defined ask is easier to accept without feeling it’s an imposition.
What if ten minutes genuinely isn’t available?
Then look for it inside something that already happens: five minutes in the car before going inside, movement while waiting at an appointment, breathing exercises during a routine task. Recovery that’s embedded in existing time doesn’t need to be carved out.
How do I know if this is burnout rather than tiredness?
Burnout tends to show as emotional numbness, resentment, feeling detached from the person you’re caring for, and exhaustion that rest doesn’t touch. Tiredness improves with sleep; burnout doesn’t. If the second one describes you, that’s a reason to speak to a doctor rather than push harder.
Is respite care worth arranging even for short periods?
Yes, and it’s consistently underused. Even a few hours weekly has a measurable effect on caregiver strain. Many regions have services that are cheaper or more available than people assume - a local caregiver support organisation is usually the fastest way to find out what exists.
How do I handle the guilt of taking time?
By reframing it accurately rather than arguing with the feeling. Caregiver capacity is a finite resource that the person you care for depends on. Maintaining it is part of the job, not a competing interest - and the guilt usually passes within a few minutes of sitting down anyway.
TL;DR:
- September stacks new demands on a caregiving baseline that never reduced, while informal support disappears
- Protect sleep timing first, then one short daily block, then movement that needs no logistics
- Ten protected minutes daily beats an hour you’ll never actually get
- Attach the block to an existing fixed point, name it in the calendar, and decide in advance what it’s for
- Ask for specific, time-bound help - open-ended requests reliably produce nothing
- Book your own health appointments alongside theirs so they don’t get dropped
The time won’t appear. It has to be taken, and ten minutes is a legitimate amount to take.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
